








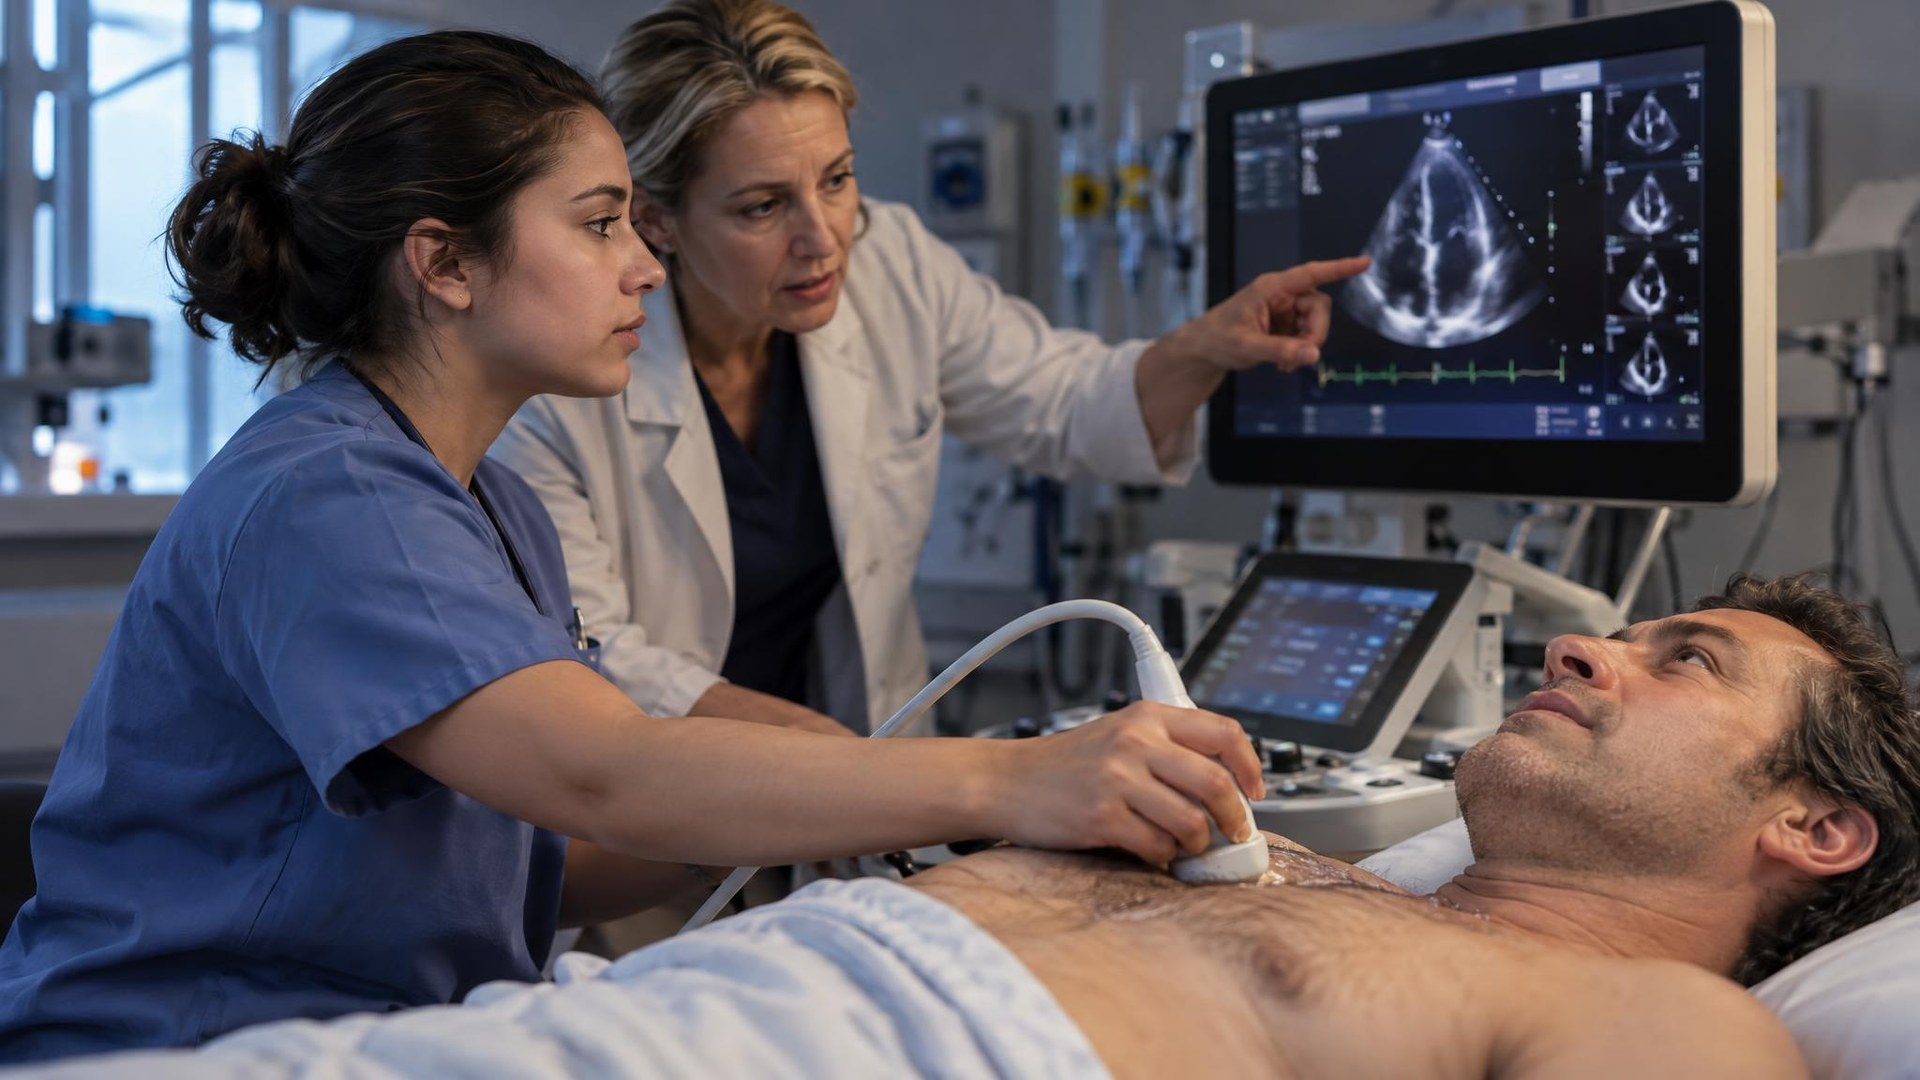

A systematic review and meta-analysis by Bijay Bastola and colleagues, published November 16, 2026, in BMC Cardiovascular Disorders, estimated a pooled diagnostic-quality echocardiography yield of 96.3% for novice and nonexpert operators using real-time AI guidance across eight studies. The measure reflects whether an acquisition met each study’s predefined adequacy threshold.
Results diverged sharply by deployment. Six studies conducted under controlled or structured conditions produced a pooled yield of 98.0%, with a 95% confidence interval of 96.7% to 99.2%. Two decentralized, real-world community studies pooled to 63.7%, with a 95% confidence interval of 20.6% to 92.6%; their individual yields were 44.8% and 79.8%. A meta-regression found the subgroup difference statistically significant at p
The authors treated that comparison as post hoc and exploratory, not preregistered. Deployment setting was intertwined with supervision, training, operator backgrounds, patient selection and outcome definitions, so the analysis does not establish setting as the cause. With only two community studies, the lower estimate is descriptive rather than a predictable success rate for future programs.
What the Review Measured
The analysis covered 2,365 examination-, scan-, or image-level observations acquired by 74 operators who had no prior formal echocardiography training or certification. Eligible studies involved real patients and AI guidance during acquisition itself, not automated interpretation of images captured earlier. The evidence spanned five AI systems and multiple operator types, from nurses and non-clinical research staff to medical trainees, general practitioners and community health workers.
Two reviewers independently searched PubMed/MEDLINE, Google Scholar, Embase, Scopus and ClinicalTrials.gov, with the final update on September 27, 2026. A second statistical model estimated an overall yield of 93.0%; sensitivity checks using different study sets, outcome definitions and statistical methods ranged from 91.2% to 97.8%. The principal estimate’s 95% confidence interval was 85.5% to 99.3%, and substantial differences between studies led the authors to warn against treating the overall estimate as a universal yield for new deployments.
Image Adequacy and Clinical Outcomes
Independent expert readers judged image adequacy in five studies. The other three defined adequacy as the AI software successfully generating an automated left ventricular ejection fraction readout, a measure of heart function, so the system being evaluated also determined the outcome. Not every observation represented a separate patient: six studies reported examinations, one counted 60 scan attempts in 10 patients, and another counted 954 images from 159 patients.
Because nearly all included studies were single-arm, the results show what novices achieved with AI guidance rather than how much the guidance added over unaided acquisition. Diagnostic-quality acquisition also is not equivalent to an accurate diagnosis, and none of the studies reported effects on clinical management or patient outcomes.
The reviewers identified operator training, supervision, image-quality checks and quality assurance as priorities for wider deployment, and called for comparative real-patient studies linking image adequacy to diagnostic accuracy and outcomes. For screening programs, the practical implication is that trained nonexperts can feasibly acquire images under structured protocols, while broader deployment still needs evidence that reliable acquisition can be reproduced in community settings and that the resulting images lead to accurate diagnoses and improved patient outcomes.
Credit: Source link